pianist and medical doctor

Tag: 2019-03

  • 01(23): The over-emphasis of patient autonomy under the guise of patient-centred care

    One of my modules this semester is titled “Communication for Improved Patient Care”. Yesterday, we had a lecture from 1-2pm, followed by a workshop from 2-4pm. The theme for this week was “Creating the right therapeutic environment”.

    When delving into the realm of medical ethics and the nature of the relationship between doctor and patient, it behooves us not to neglect the work of Beauchamp and Childress. I quote from reference [1]. They are American philosophers best known for their work in medical ethics. Their book Principles of Biomedical Ethics was first published in 1985, where it quickly became a must read for medical students, researchers, and academics. The book was written in the wake of some highly unethical biomedical experiments – most notably the Tuskegee Syphilis Study, where hundreds of rural black men, their partners, and subsequent children were infected or died from treatable syphilis. Beauchamp and Childress aimed to identify healthcare’s “common morality”.

    The four principles that they established were: 1) Respect for autonomy; 2) Beneficence; 3) Non-maleficence; 4) Justice. With these principles, it is not difficult to see why the Tuskegee Syphilis study was deemed outrageously unethical. Some will claim that morality is subjective and that the weighing of these different ethical principles, which are often in tension with one another, is subjective. What I will talk about in this post is not about whether these principles are valid. Debating the innate fundamental validity of these principles, or even whether morality is subjective, is something probably best left to the devices of philosophers and theologians. In this post, I instead make the assumption that these four principles are all valid principles to be considered in the context of modern evidence-based medical practice.

    During the tutorial, we were told to get into pairs or trios, as part of one of the initial activities, to discuss the question: “What is meant by patient-centred care?” I started by first sharing with my group partner how the term is somewhat self-explanatory. Patient-centred care would just mean placing the patient’s needs and welfare above all else to ensure optimal patient outcome. It’s so simple. What could possibly go wrong?

    Reality is not so straightforward. The tutor voiced her disagreement regarding one of the points I made (I shall elaborate on this soon) in front of the entire tutorial group during the tutorial. The disagreement probably stemmed from misunderstanding as there wasn’t enough time for me to fully explain my views. Hence, I have written this post.

    The impression I got from her was that she views patient autonomy as being the most important thing to consider in the context of “communication for improved patient care”. Understandably, she might feel this way due to the nature of the topic and perhaps, even some past experience where she feels that her autonomy should have been emphasised. I am not her and I cannot say with certainty what she thought, and so I’m merely speculating.

    In the context of patient communication, we cannot directly control the minds of patients and influence their responses and behaviours. What we can change, however, is what we can do on our part (eg our diction, our tone, our body language, our holistic response). For example, you may encounter an unreasonable patient who raises his voice and shouts at you during the consultation. In such a scenario, it would be inappropriate to respond likewise. Raising your voice at the patient as a way to vent your frustration will likely land you in trouble. It will likely provoke an even more emotional response from the response, and this will not help in de-escalating the situation at all. The last thing you want is a letter of complaint from the patient which ultimately gets you berated from your superior, which might in turn cost you your job. What you can do, however, is to insist on behaving in a professional manner and adhere to a standard of decorum which is expected of a medical practitioner.

    While optimal patient care requires both the patient and doctor to play their part, the sole focus tends to be on what the doctor can do, at least for this particular module I’m currently taking. After all, the patient tends to be passive while the doctor tends to be active. Some people talked about the power differential between the doctor and patient; some talked about the state of vulnerability of the patient.

    I talked to my group partner about a hypothetical scenario where there are two treatment options for a patient’s condition. Let us suppose first that hypothetically, all options work equally well given the patient’s condition, and that treatment A and B cost $50 and $100 respectively. Patient-centered care in this context would mean explaining to the patient that both options work equally well and that treatment A costs less than B. The rational patient would likely choose the former option since it is more affordable and it works just as well as the more expensive option. Everyone lives happily ever after. Simple, right?

    Let me now introduce you to something slightly more realistic. What if Treatment B works better, and that it improves the patient’s quality of life more than A? You explain how both treatments to the patient and the patient gives informed consent to proceed with a particular treatment. The patient’s autonomy is respected. Even if the patient rejects either treatment, the doctor accepts it and the patient’s autonomy is respected, and everyone still lives happily ever after. Still simple, right?

    I talked about this issue with my group partner. Specifically, I talked about how certain medications can be administered to lower peripheral vascular resistance, so as to treat hypertension by lowering blood pressure. Blood pressure in our bodies is governed by the equation BP (Blood Pressure) = CO (Cardiac Output) * PVR (Peripheral Vascular Resistance), which can be further broken down to BP = SV (Stroke Volume) * HR (Heart Rate) * PVR. There are so many things you can do to influence blood pressure in the body. Let’s talk specifically about PVR (Peripheral Vascular Resistance).

    With the equations above, you can lower BP by lowering the vascular resistance. There are at least three ways you can lower the PVR.

    According to a doctor who knows well how hospitals in Singapore operate, treatment 1 is relatively affordable. Treatment 2 is moderately priced. Treatment 3 is relatively expensive. In Singapore, at least, Treatment 1 tends to be given more in public hospitals whereas Treatment 3 tends to be given more in the private hospitals. These treatments have different levels of effectiveness in people with different conditions. Do you see the different principles at play here? As much healthcare providers would like to provide quality patient care, there are other considerations, particularly so for public hospitals which have more red tape and standard operating procedures. Resources are scarce and subsidies are limited. Who gets to decide what constitutes an equitable distribution of resources? How much subsidy should a patient receive? Means-testing? How then is the criteria decided? There are endless questions one can ask. Many stakeholders are involved, and the ever-changing laws and advancements in medical technology just further complicate matters. These issues cannot be analysed as though they constitute a static cross-section in the moving tubular fabric of time.

    Still manageable? Well, let me now bring you to murkier waters. I want to discuss informed consent, which is a sacred cow in healthcare. There is information asymmetry between a doctor and his patient, and this was the point of disagreement and contention between my tutor and me. I said that a doctor is likely to have a far better understanding of the patient’s condition than the patient, and objectively speaking, it is the doctor who has a much better chance of making the informed decision. After I raised this, she immediately said that she disagreed. She talked about how the patient also considers the non-medical aspects of his situation. For example, in deciding which treatment to get, or whether to even get treatment, a patient would also consider whether he would be able to cope with his work/daily activities as he would have to deal with the side effects of the treatment. Finances are involved too. Medicines can be quite expensive and insurance plays a huge part. Insurance policies are notorious for their fine print and it doesn’t help that there are so many types of insurance policies. The patient’s policy might not cover a particular treatment. In this aspect, I agree with the tutor regarding how the patient is and should able to make an informed decision because of two reasons:

    1) There should be respect for patients’ autonomy.
    2) The patient knows and understands the non-medical aspects of his life more than the doctor. In this sense, the patient can take into account the medical and non-medical aspects of his life when making a decision whereas the doctor will only have a superficial understanding of the patient’s non-medical aspects. Regarding the non-medical aspects, the doctor is limited by what the patient tells the doctor. However, the caveat is that the patient’s understanding of the medical aspect of his condition is limited by how much his doctor tells him about the condition and how much the patient understands what the doctor is telling him.

    However, there is one factor that we cannot neglect in the above scenario:

    Externalities.

    If my tutor insists on the notion of giving utmost precedence to patient autonomy without carefully weighing the impact of these externalities, I would have to respectfully disagree with her stance. There are externalities associated with different treatment options or rejection thereof. These externalities can be positive or negative, and externalities bring us directly to the heart of the tension between the four principles. If patient autonomy were given utmost precedence under every circumstance, the issues of anti-vaccine groups, abortion, euthanasia would not even be controversial. In Singapore, it is compulsory for a child to be vaccinated against measles and diphtheria. If patient autonomy (in this case, the parent decides on behalf of the child) were to always take precedence, why is it then legally mandatory for children to be vaccinated against measles and diphtheria? After all, shouldn’t they have the right to reject the treatment? Haha.

    These are highly contentious issues, and we need to remember that patients’ decisions regarding medical treatment often do not just affect themselves but also the people around them, the general public, and even another powerless entity whose life depends on the patient (in the case of abortion).

    In addition to the issue of externalities, another thing for us to consider is the power differential between doctors and patients. When you go beyond the clinical setting and consider the big picture, saying that doctors are always in a position of power and authority over their patients is an oversimplification. Patients have ways of getting back at their healthcare providers in the form of complaints, litigation, etc. Allow me to quote from an article entitled “Things are looking up for the medical profession. Really.” written by Salma Khalik, Senior Health Correspondent, published on 21 March 2019 by The Straits Times (reference [4]), regarding the case involving a $100,000 fine:

    In January, a doctor was fined $100,000 for not telling his patient about the side effects of a steroid jab, which is fairly common injection. The disciplinary tribunal said it was the correct treatment, but took exception to his not telling the patient about the possible side effects, which she suffered from. An expert witness during the hearing said that while it is good practice to do so, not all doctors do, since the side effects are both rare and transient.

    The judgment and the size of the penalty upset doctors in both the public and private sectors. Some wrote in to the Forum pages, others signed a petition to the MOH, and the subject was also raised in Parliament.

    In the light of the two recent cases in Singapore, we see that doctors don’t take that high-and-mighty role all the time. Even when they act reasonably in good faith, they can be subject to disciplinary tribunals, litigation, and can be meted out with unreasonably harsh penalties. Do we really want to see defensive medicine in Singapore, where doctors order excessive tests, create more paperwork and forms to sign, spell out the comprehensive list of side effects for even ubiquitous drugs such as paracetamol to avoid getting sued and avoid having to pay exorbitant sums of money? This will only bloat the healthcare sector, particularly the public sector, with more inefficiency, smother everyone with red tape, and ultimately cause healthcare costs to skyrocket.

    In conclusion, while I do believe that patient-centered care is a noble objective that doctors must strive for, it is quixotic to take this to the extreme by insisting that the patient’s desires and views must be at the forefront at the expense of other factors that need to be considered. Respect for the patient’s autonomy is one thing, but what about beneficence, non-maleficence, and justice? The needs and limitations of other people, in addition to his patient, need to be considered carefully as well. These principles are often in tension with one another and drawing the line is not easy. Patients should acknowledge that the doctor does not have an easy time as the doctor needs to carefully weigh all these factors because he is not just accountable to his patient alone; he is also part of a network of healthcare providers which is responsible for the healthcare of an entire population.

    Yours faithfully,
    Nicholas Loh
    22 March 2019

    P.S. (2019-03-22, 2:16pm, ACDT) One of the readers of this post, a medical student, has given valuable feedback. He talked about how in the context of Singapore’s healthcare, some older patients are more accustomed to medical paternalism, and I think it is good for medical students to be aware of this. Hence, they can be somewhat shocked when they are confronted with “choices”. They have grown used to having the physician as the authority figure who knows what is best for them. Hence, they can be taken by surprise. What is the physician then to do? Can there truly said to be “informed consent” in this scenario? I contemplated discussing in this post the Bolam and Montgomery tests. However, I decided against it as to do the issue justice would require a separate blog post!

  • 01(22): I finally met you

    “Don’t forget to complete questions 3 to 7a. We shall be going through them on Thursday! Remember this, I can’t help you if you choose not to help yourself. So please, be true to yourself!” reminded Mr Toh, our Physics teacher. As the school bell sounded like it always did on the hour, my classmates erupted into incessant chatter, likewise with the other classrooms adjacent to ours. Lorraine, who sat nearest the door, immediately faced towards the diagonally-opposite corner of the class, and tried to catch the attention of Jolene, her best friend. “Jo!” Lorraine beckoned. “What do you wanna do later?!”

    Lorraine’s shrieks faded into the background as I made my way out of the classroom, trailing Mr Toh. With some effort, I jostled through the pairs and trios of students who were walking along the corridor. Disgruntled, I made my way to the ground floor. Surrounding me were class benches.

    It was the same old sight every day. In their cliques, girls engaged in gossip. People charged their portable chargers at the wall sockets while they perused their lecture notes. The same people had their earbuds fitted nicely, with which they enjoyed what was supposedly their favourite music. Unattended laptops, phones and other valuables lay atop the class benches. And yes, I know, I know – how can we forget that group of people – the same old familiar faces masquerading around school. Though they didn’t hold hands (which they were certainly not allowed to), it was obvious to anyone with half a cerebrum that they were couples. In the evening, some of these couples even shared earbuds, that they might listen to the same music while “studying”. The sight went in stark contrast with what my father described to me when he himself was a student. When he was in my shoes thirty years ago, things were different. Back then, discipline and order were apparently upheld and championed with pride. Even girls were only allowed to have short hair. C’est la vie. As for whether the past could be coined “the good old times”, well, that’s ultimately up to our imagination, isn’t it?

    At that moment, I couldn’t help but recall a picture I had chanced upon online. The picture was divided into four quadrants. Each quadrant contained one sentence. Strong men lead to good times. Good times lead to weak men. Weak men led to bad times. Bad times led to strong men. One-sided arrows connected the quadrants. Chuckling to myself, I made my way to the gate at the side of the school led me on my way to the nearby Starbucks joint.

    As I opened the glass door to the Starbucks joint, the gush of cool air comforted my face. In its embrace, I was there and then relieved of the discomfort from the beads of perspiration that had been cascading down my forehead and cheeks.

    Oh, thank God for the air-conditioner.

    I headed towards one of the chairs and promptly set my brown leather sling bag on it. After glancing around, I then glanced at my watch at the flick of a wrist. Hmm. It was barely a quarter past one.

    Shouldn’t there be more of a crowd? Well, in that situation, I wasn’t one to complain. This was a blessing.

    “What you want today sir?” hissed the bespectacled woman who donned a sulk on her face. Well, there can never be enough negativity for one day huh.

    “Do you do Trentas here?”

    “Huh? Tlenta ah? That is what ah? Got such thing meh?” she replied, baffled.

    “Never mind then. A Venti Iced Teavana Shaken Strawberry Green Tea Infusion Lemonade with sugar and caramel syrup.”

    “Huh? Sorry can repeat again?”

    That phrase bugged me. The word “again” is redundant, unless of course, I had already repeated myself, something I clearly had not done.

    After successfully completing that unusually arduous task which seemed to take aeons, I proceeded to my seat and whipped out the tutorial questions that I had to complete by Thursday. While I don’t normally do schoolwork in places like Starbucks, this time was different. Somehow, I felt that I should just complete it before going home.

    I opened the booklet containing the tutorial questions, while also laying beside it ruled paper. Just at that moment, the door swung open, initiating the chime of the miniature bells that adorned the top of the door frame. In walked a girl whose hair was neatly tied into a ponytail, with a black hairband holding it in its place. The badge on the left collar of her beige blouse was no strange sight. Though I knew not her name, I had seen her frequently, albeit from a distance, as I traversed the school premises. It must be something like the Baader-Meinhof at play here. Given her petite figure, I doubt she would even order half of what I ordered.

    “A Short Iced Coffee please, and also, without sugar or syrup”, she remarked, with a smile plastered on her face. As expected – how predictable.

    She soon returned to her seat which was three seats on my right. While sipping on her coffee, she glanced out of the window, looking at the vehicles zipping past along the road, all while maintaining her pleasant smile, as her visage basked in the glory of the majestic limpid sunlight that filtered through the speckless windows. Putting her cup of coffee down, she soon began to glance around the joint, just like I had done. Briefly, just so ever briefly, our curious eyes met.

    I immediately darted away. It soon dawned on me how long I had spent gazing at her – from a distance. Oh dear. I certainly hope she didn’t think I was a creep. That was certainly not a first impression of myself that I intended to establish. What’s wrong with choosing to be more cognizant of one’s surroundings?

    I started doing the tutorial questions. Yet, I yearned to talk to her. Who was she? I simply wanted to know the name of someone whose face I kept seeing. I could not focus on the questions that lay on the table. Though they were right before my very eyes, they were taunting me.

    I glanced back at her.

    With her left thumb holding a verso and a recto of a paperback apart, she gently sipped on her coffee once again. That was it. I was going to walk up and talk to her. Thoughts were running through my mind. “What if she just stares at me upon approaching her?” Anxiety coursed through my veins. “What if she just stands up and walks away without saying a word?” After overcoming the internal cognitive dissonance, I mustered whatever ounce of courage I had in me. With the faith of a mustard seed, I departed for her table (which was technically my table since all the seats shared a single long table). No sooner had I taken three steps than she glanced at me in surprise. However, upon arriving at her seat, whatever courage I had was now depleted.

    “Hey, my name’s Nic. I couldn’t help but notice you when you walked in. You see, I somehow notice you a lot lately on campus, I mean…not that I actively look for you, but…”, I stuttered slightly in a way that was not representative of my usual coherence.

    Mmmmm. Pretty sure she donned a Gucci Bloom – a rich floral scent that suits her so well. I was now close enough to her that I could see in full view her dark hazel iris and sharp gaze as though her eyes lined with shards of glass around the edges. The calculating coldness at the centre of her pupils drew me closer.

    She put her book down, with the front cover against the cool surface of the pine table. The look of surprise soon morphed into one of serenity. And now, this time, though her lips were delicately against each other, she sat there smiling. Those few seconds of silence felt like an eternity. How was she going to reply? To say that I had mixed emotions was an understatement. There she sat, smiling at me. I wonder if she knew the effect that she was currently having on me. The dimples on her cheeks now further catalysed the melting of my heart. Yet. Yet, I could feel my heart palpitating with trepidation, as consternation and uncertainty engulfed my thoughts. Soon, she spoke with a delicate and mellifluous voice that caressed my earlobes like the petals of a rose.

    “I was wondering when you would approach me”, she beamed.

  • 01(21): Ms, Miss, Mrs, and Madam. What’s the difference?

    My Primary One English teacher was addressed by us students as Mdm Siti. In secondary school, I had a Chemistry teacher who wished to be addressed as Ms Ngo. Then, when I was in Primary Four, I had a teacher who was to be addressed as Mrs Loh. On the other hand, addressing my male teachers was so much more straightforward. Women have it more complicated than men in many aspects of life. Of the many aspects, the aspects of titles is one. Before we discuss the distinctions between the various forms of social address that women have, permit me to first discuss social titles given to men.

    Consider the name: Mr John Smith. The typical man would have the title “Mr”. This is the most common honorific for men under the rank of knighthood. “Mr” is an abbreviation of “Mister”; the title derives from earlier forms of “master”. On the other hand, men who are knighted are addressed with the honorific “Sir”. For example, after Mr András Schiff was knighted in 2014, he became known as Sir András Schiff.

    There is another honorific for males, albeit highly traditional. You won’t ever hear it in Singapore, but you might still hear it within conservative circles in the UK. That honorific is “Master”, and it is used as an honorific for boys and young men. Typically, when you imagine a young boy being addressed as “Master”, you would conjure a typical movie scene of a butler in a wealthy household addressing the young son of the head of that household. I quote from the Wikipedia article for the honorific “Master”:

    “Master” was used in England for men of some rank, especially “free masters” of a trade guild and by any manual worker or servant employee addressing his employer (his master), but also generally by those lower in status to gentlemen, priests, or scholars. In the Elizabethan period, it was used between equals, especially to a group (“My masters”), mainly by urban artisans and tradespeople. It was later extended to all respectable men and was the forerunner of Mister (Mr).

    After its replacement in common speech by Mister (Mr), “Master” was retained as a form of address only for boys who have not yet entered society. By the late 19th century, etiquette dictated that men be addressed as Mister, and boys as Master.

    In regions which abide by British tradition, abbreviated forms of social titles and degree titles generally do not contain periods between the letters (eg Mr/Dr/MD/PhD/BS/BA). On the other hand, it is customary in the US and places influenced by US tradition for there to be periods between the letters (eg Mr./Dr./M.D./Ph.D./B.S./B.A.). Singapore abides by the British tradition. Hence, we do not have periods after titles.

    Having established what it is like for men, let’s talk about the titles that women need to deal with. To begin, the titles “Ms”, “Miss”, and “Mrs” all ultimately derive from the term “mistress”, which dates to the 15th century. Here are some example texts from the OED (Oxford English Dictionary):

    1463 in S. Tymms Wills & Inventories Bury St. Edmunds (1850) 36, I … be qwethe to my maistresse Clopton a spoon of berell.

    1471 J. Paston in Paston Lett. & Papers (2004) I. 443 Iff it come to Mestresse Elysabeȝ Hyggens … sche schall comveye it to me.

    Today, the use of “mistress” to denote a married woman is now the least common meaning of the word.

    “Miss” is an honorific for young women (typically under thirty years of age) who are unmarried. It can also be used as a form of address. This is increasingly uncommon, as “Ms” becomes increasingly popular. The distinction between “Miss” and “Mrs” became problematic with the rise of feminism and more opportunity for women as more women entered the white-collar workforce. Women who became famous before marriage often kept their birth names, stage names, pen-names, or pseudonyms.

    “Mrs” is an honorific that is reserved for married women. Very traditionally, this is used along with the husband’s first and last name. For example, if John Smith were to marry Jane Doe, Jane Doe will be referred to as Mrs John Smith. However, it is now quite uncommon for a woman to be addressed by her husband’s first name. Typically, a woman is addressed by her husband’s first name only when they are addressed jointly. For example, “Mr and Mrs John Smith were invited to the gala”. Many married women now adopt only their husband’s last name after marriage. For example, Jane Doe would be referred to as Mrs Jane Smith after marriage. Here is a quote from the Wikipedia article which elaborates on the use of “Mrs”:

    In several languages, the title for married women such as Madame, Señora, Signora, or Frau, is the direct feminine equivalent of the title used for men; the title for unmarried women is a diminutive: Mademoiselle, Señorita, Signorina, or Fräulein. For this reason, usage had shifted toward using the married title as the default for all women in professional usage. This had long been followed in the United Kingdom for some high-ranking household staff, such as housekeepers, cooks, and nannies, who were called Mrs as a mark of respect regardless of marital status. However, in the late 20th century the marital-neutral Ms became more common for women professionally and socially.

    According to Wikipedia, “Ms” arose in the 1970s when this term started being used by those seeking to diminish the importance of marriage to a woman’s social identity. When in doubt, just use this title. You can’t go wrong because “Ms” is neutral and would be equivalent to the male “Mr” as it is not marriage-dependent.

    Now, for the last one, we see the clash of cultures in Singapore. Singapore is in many aspects, the interface of the East and the West. This is where the term “Madam” or the abbreviated “Mdm” comes in. A variant of “Madam” is “Madame” and it comes from the French term “ma dame” which means “my lady”. In Southeast Asia, it is traditional for women to continue using their maiden name after marriage. It is not uncommon to see women being addressed by their maiden surname after “Madam”, while women would be addressed by their husband’s surname after “Mrs”. Women who use “Mrs” over here are typically more inclined to Western culture and influence. Of course, there are inconsistencies too. I know this particular woman whose maiden surname I know not. Hence, I address her as Mdm Tan (her late husband’s surname is Tan). Remember my Primary One English teacher I mentioned in the first paragraph? I’m pretty sure “Siti” is her given name and not her last name.

    Take-home message: Aren’t you awed by the sheer amount of historical baggage that accompanies women’s honorifics? So many of these developments occurred because of societal norms which changed over the years. Some people (eg divorcees, single unwed mothers with children, older women who were unmarried) did not fit nicely into the categories which society had established. Furthermore, conventions from other languages have also influenced the use of these titles in English. The culture and history of a region does play a big role in how honorifics are used. As such, there have been inconsistencies regarding how the titles were used and are being used across the women, particularly for women.

    Ultimately, a woman chooses a particular title for herself probably because she feels that it best reflects her values, beliefs, and current position.

    Ask her how she wants to be addressed if you are unsure!

    Yours faithfully,
    Nicholas Loh
    19 March 2019

    References
    1. https://en.wikipedia.org/wiki/Mr.
    2. https://en.wikipedia.org/wiki/Master_(form_of_address)
    3. https://en.wikipedia.org/wiki/Mrs.
    4. https://www.grammarly.com/blog/ms-mrs-miss-difference/
    5. https://blog.oxforddictionaries.com/2011/11/02/what-are-mrs-and-ms-short-for/
    6. https://en.wikipedia.org/wiki/Madam

  • 01(20): The irony of the innominate artery, and other things

    One of my topics this semester is Pathophysiology. According to the topic co-ordinator, the “purpose of this topic is to introduce you to the pathophysiology of the cardiovascular system with a special interest in Acute Coronary Syndrome (ACS) & ECG Interpretation. The cardiovascular system is an integral part of every patients’ [sic] presentation and understanding its function in health and disease is essential for optimal assessment and managment [sic] of your patients. This topic will briefly review cardiac A&P, then analyse the cardiac conduction system and what happens when it becomes pathological in cardiac emergencies such as ACS, STEMIs & cardiac failure.”

    The content this week consisted of a review of cardiac anatomy and physiology. Allow me to share some stuff I found interesting.

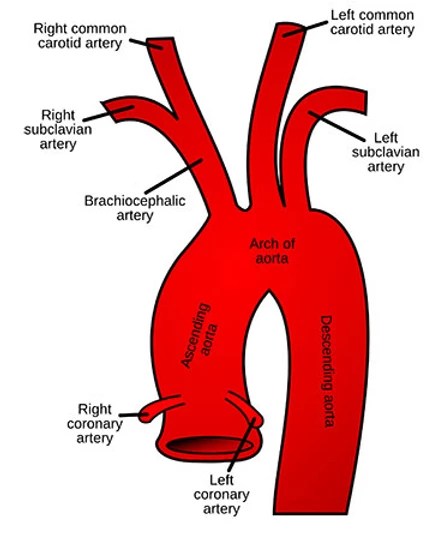
    1. Below is an image that depicts some of the main branches of the aorta.

    What I wish to talk about is the brachiocephalic artery. Did you know that apart from its alternative name, brachiocephalic trunk, it has yet another name? The brachiocephalic trunk is also known as the innominate artery. How ironic. Yet, it is interesting to note that “brachiocephalic artery/trunk” started getting coined earlier than “innominate artery”. Why then is this trunk described as “brachiocephalic”? As I discussed in a previous post, a lot of medical jargon consists of Greek and Latin roots cobbled together. In this case, the term “brachiocephalic” can be broken down into “brachio-” and “-cephalic”. The former and latter terms mean “arm” and “head” respectively. It is easy to see how in many cases, the name of something gives a clue as to its function. It is thus not surprising to learn that the innominate artery supplies blood to the right arm, head, and neck.

    2. Another thing I found interesting was the word coronary. Why are the coronary vessels described as “coronary”? For a long time, I thought this adjective came from the Latin word for heart – “cor”. However, the true etymology is such that the word comes the Latin word “corona”, which means “wreath” or “crown” (cf Elizabeth II’s coronation in 1952).

    In the image above, the green line is the interface of contact between the crown and the person’s head. The way the right and left coronary arteries encircle the heart makes the term “coronary” an apt descriptor.

    3. What do you know about the coronary dominance of hearts?

    As I watched the video, this diagram came up. What is depicted above is the most typical form of the heart. Here, the posterior interventricular artery branches from the right coronary artery. However, as I saw this diagram, I thought to myself: “Wow, the end of the right coronary artery is so close to the end of the circumflex artery. I wonder if they join together, in some people, to produce a true “crown” that encircles the heart.”

    Regarding coronary dominance, according to the video at least, dominance of the coronary arterial system is defined by which artery gives rise to the posterior descending artery (PDA)/posterior interventricular artery. Apparently, the PDA arises from the RCA (see image below) 60-80% of the time. Hence, we don’t normally talk about a “right dominant heart” because that is usually the assumption.

    In a minority of people, the PDA arises from the circumflex artery, which ultimately comes from the left coronary artery. The hearts of such people would be termed “left dominant”.

    In an EVEN smaller minority of people, the PDA would arise from both the circumflex artery and the right coronary artery. Such people are said to have co-dominant hearts.

    Interesting, isn’t it? It turned out my intuition was right after all. Haha.

    Yours faithfully,
    Nic Loh
    8 March 2019

    References
    1. https://www.youtube.com/watch?time_continue=488&v=xSnFf62GDBI